

The science behind bedtime meltdowns, racing thoughts, and why evenings are so much harder. Here’s what actually helps.
 Dr. Aryeh Berlin, PsyD
·
 14-minute read
·
 Research-based
·
 For parents of anxious children
You’ve made it through the day. Homework is done. Dinner is over. And then bedtime arrives. And so does the anxiety.
The worries that seemed manageable during the day suddenly feel enormous. Your child needs one more hug, one more glass of water, one more reassurance. They can’t sleep alone. They can’t fall asleep at all. And they’re exhausted (so are you), but the anxiety won’t let them rest.
This isn’t you failing at bedtime routines. There are real, well-researched reasons why anxiety reliably intensifies at night for children. Understanding those reasons is the first step toward actually doing something about it.
- Refuses to sleep alone or needs you in the room to fall asleep
- Has meltdowns, crying spells, or panic at bedtime
- Repeatedly asks for reassurance about bad things happening at night
- Seems fine during the day but anxious only after dark
- Wakes frequently from worry, nightmares, or fear
- Anxiety gets worse at night because the distractions that hold it back during the day disappear
- Anxious children are biologically wired to stay alert for danger, and nighttime gives that instinct nothing to compete with
- Poor sleep and anxiety feed each other in a cycle that keeps both going
- CBT and gradual exposure are the most effective treatments, especially when parents are actively involved
Why Anxiety Gets Worse at Night: The Science
Nighttime anxiety isn’t random. It isn’t a phase children grow out of automatically, and it isn’t just about monsters under the bed. Research points to several converging mechanisms that make the hours before sleep reliably harder for anxious children.


The Distraction Buffer Disappears
During the day, children are busy. School, homework, activities, and social interaction keep the mind occupied. These aren’t just pleasant distractions. They’re neurological competition. Engaging tasks prevent the brain from turning inward and dwelling on worry.
Bedtime removes all of it at once. The lights go down, the house gets quiet, and suddenly there’s nothing competing with the anxious thoughts. Research on perseverative cognition (the tendency toward repetitive, recycling worry) shows that without competing stimuli, anxiety-driven rumination intensifies at sleep onset. What felt manageable at 4pm feels catastrophic at 9 or 10pm. This isn’t dramatic. It’s neurological.
Studies using neurocognitive models of insomnia show that heightened worry at bedtime promotes maladaptive responses, like ruminating, seeking reassurance, or delaying sleep, that over time become conditioned responses. The bed itself becomes associated with anxiety rather than rest.
Anxious Children Are Already on High Alert
Children with anxiety disorders don’t just worry more. They’re biologically oriented toward scanning their environment for threat. Research using eye-tracking with anxious children ages 9–14 found that this vigilant attention to threat directly predicted longer time to fall asleep and more nighttime wakings.
During the day, this hypervigilance can blend into background noise. At night, in a dark room with no competing stimuli, there’s nothing to distract from the threat-scanning. Every creak, every shadow, every unusual sound gets processed through an already-activated alarm system. The result: a brain that won’t quiet down, in a body that desperately needs sleep.
|
3 in 4
anxious kids still have significant sleep problems even after their anxiety treatment ends
|
416K+
adolescents studied confirm: sleep problems and anxiety strongly predict each other
|
58%
more likely to have anxiety in adolescents who are naturally wired to stay up late
|
The Sleep–Anxiety Cycle
One of the most important things parents need to understand: the relationship between sleep and anxiety runs in both directions. Poor sleep doesn’t just follow anxiety. It also causes anxiety to worsen.
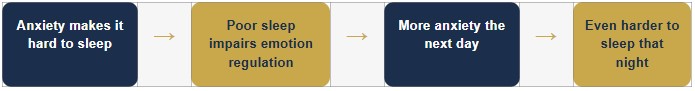
This means that treating only the anxiety, without addressing the sleep disruption it causes, can leave families stuck in a cycle. Anxiety drives poor sleep. Poor sleep impairs the emotional regulation capacity children need to manage anxiety the next day. And so it continues.
A Special Note on Adolescents
Adolescence adds another layer. The prefrontal cortex, the part of the brain responsible for regulating emotional reactions, planning, and impulse control, is still actively developing through the mid-20s. At the same time, the subcortical structures that generate emotional reactivity are at peak activity. Teenagers are literally running emotional responses on underdeveloped regulatory hardware.
There’s also the body clock factor. Adolescents experience a biological push toward later sleep and wake times. When teens are forced into bedtimes that fight their internal clock, it creates real physiological tension, one that research associates with higher anxiety levels and more nighttime distress.
A teenager who won’t go to sleep at 10pm may not be defiant. Their biology genuinely pushes toward a later schedule. This doesn’t mean screens at midnight are fine, but it does mean that extremely early bedtimes for teens can amplify nighttime anxiety rather than reduce it.
A Note on Sensory Sensitivity and Younger Children
For preschool-aged children especially, there’s an additional factor worth knowing about: sensory sensitivity. Research published in 2026 found that children with anxiety disorders show higher levels of both irritability and sensory over-responsivity than children without anxiety, and that these factors independently predicted sleep difficulties.
In plain terms: some anxious young children are physically more reactive to sensory input, sounds, textures, light, temperature. At bedtime, when those inputs aren’t buffered by activity, they can feel genuinely overwhelming rather than merely annoying. For these children, environmental adjustments (white noise, blackout curtains, specific bedding textures, a cooler or warmer room) aren’t just comfort measures. They’re clinically relevant.
What Actually Helps: Evidence-Based Approaches
The good news: nighttime anxiety in children is one of the most thoroughly studied and treatable presentations in child psychology. The research is clear on what works, and it involves significantly more than putting a nightlight in the room.
Cognitive Behavioral Therapy (CBT): The Foundation
CBT is the first-line, evidence-based treatment for childhood anxiety disorders, including presentations where nighttime is the primary problem. The American Academy of Child and Adolescent Psychiatry recommends it as the starting point for mild to moderate anxiety. The most comprehensive research review on CBT for child anxiety (the Cochrane review, covering 87 studies and nearly 6,000 children) found that roughly 1 in 3 children benefit who otherwise would not recover without treatment.
CBT doesn’t just teach kids to “calm down.” It works across three dimensions that directly drive nighttime anxiety:
|
1
Cognitive Restructuring
Identifying the distorted thoughts that spike at bedtime: catastrophizing, mind-reading, worst-case predictions. Learning to evaluate them accurately.
|
2
Graduated Exposure
Systematically and gradually facing feared situations, including sleeping alone, handling dark rooms, tolerating nighttime sounds, in a structured, supported way.
|
3
Physiological Regulation
Relaxation techniques (deep breathing, progressive muscle relaxation, guided imagery) that directly lower the bodily arousal that keeps children awake.
|
A Cochrane review of CBT for child and adolescent anxiety found that more time devoted to exposure, particularly to more difficult exposure tasks, predicted significantly better outcomes. There’s also emerging evidence that beginning exposure earlier in treatment (rather than spending many sessions first on anxiety education) produces better results in fewer appointments.
For a child afraid to sleep alone, “graduated exposure” doesn’t mean forcing them to sleep alone on night one. It means building a ladder: sleeping with the door open, then closed; parent checking in after 5 minutes, then 10; ultimately reaching independent sleep. All at a pace the child can manage with support. The discomfort is real. The avoidance is the problem.
Family-Based CBT: Why Parents Matter So Much
For children under 8, family-based CBT isn’t just a nice addition. It’s classified as the most well-established treatment approach. Parents aren’t passive observers. They’re active participants in what’s maintaining the anxiety and in what will resolve it.
Research on parent-delivered CBT found that 50% of children recovered from their primary anxiety diagnosis when parents were guided through implementing the approach at home, compared to 25% on a waitlist. For children ages 5–7, approaches that involved both parent and child together were significantly more effective than parent-only treatment.
What does parent involvement actually look like? The American Academy of Pediatrics’ 2026 clinical guidance identifies several home-based approaches parents can implement:
- Normalizing anxiety without escalating it (“I know this feels scary. You can handle it.”)
- Modeling brave behavior: staying calm at bedtime rather than visibly anxious about your child’s distress
- Providing graded exposure to nighttime fears rather than removing all discomfort
- Verbal affirmations during exposure rather than reassurance that eliminates the feared situation
Reassurance and affirmation are not the same thing. “Nothing bad is going to happen” is reassurance. It targets the anxiety content and provides temporary relief while reinforcing the pattern. “I know this feels hard, and I believe you can do it” is affirmation. It validates the experience while building capacity. Over time, only one of these actually helps.
When Sleep Problems Need Their Own Treatment
Here’s something many families don’t hear enough: treating the anxiety often isn’t enough to fix the sleep. Research following anxious kids through anxiety-focused treatment found that 3 out of 4 still had significant sleep problems when treatment ended. The sleep disruption had, in many cases, become its own self-perpetuating problem.
This is why sleep-specific interventions are sometimes needed as an add-on to anxiety treatment, not instead of it. Behavioral sleep interventions that have strong evidence include:
| Strategy | What It Involves | Role |
|---|---|---|
| Consistent Sleep Schedule | Same bedtime and wake time every day, including weekends | Foundation |
| Positive Bedtime Routines | Calm, predictable pre-bed sequence appropriate to the child’s age | Foundation |
| Graduated Extinction | Progressively extending response time to bedtime resistance, without reinforcing avoidant behavior | Behavioral |
| Bedtime Fading | Start bedtime when the child naturally falls asleep; gradually move it earlier as sleep consolidates | Behavioral |
| Stimulus Control | Bed used only for sleep; if unable to sleep after ~20 min, leave and return when sleepy | Behavioral |
| Environmental Optimization | Cool, dark, quiet room; screens off at least 30 minutes before bed; morning light exposure | Foundation |
| Bedtime Pass | Child receives a limited number of “passes” to leave bed, reducing extinction bursts and giving the child agency | Adjunct |
Research on group-based behavioral sleep interventions for preschoolers found significantly greater improvements not only in sleep but also in anxiety and internalizing symptoms compared to standard care. Sleep improvements driving the subsequent reductions in anxiety. Treating sleep directly, in other words, reduced anxiety. Which reinforces the bidirectional nature of the problem, and the value of treating both.
For Younger Children: Fear of the Dark and Nightmares
For children ages 4–8, bedtime fears often have more concrete content: darkness, monsters, something under the bed, nightmares. A 2026 clinical trial tested a home-based program combining bibliotherapy with games, parent-led, 4–5 weeks, incorporating gradual exposure and nightmare management. The results showed significant reductions in fears related to nighttime and imaginary stimuli, improved nighttime behavior, and a greater ability to act independently in dark situations.
For children with recurrent nightmares, CBT for nightmares in children (CBT-NC) is a structured protocol that includes sleep education, a “worry jar” for nighttime thoughts, progressive muscle relaxation, and a technique called nightmare rescription, where the child, with support, rewrites the ending of their scariest nightmare into something they can tolerate or control.
Designating a “worry time” earlier in the evening, where the child actively writes or draws worries into a jar or journal and “closes” it before bed, has strong support as a way to contain the free-floating worry that otherwise arrives exactly at lights-out. It doesn’t eliminate worry. It creates a boundary around it.
When to Seek Professional Support
Some nighttime anxiety is developmentally normal, especially during transitions, stress periods, or at certain developmental stages. But there are signs that indicate the pattern has moved beyond normal variation and warrants a professional evaluation.
| → | Your child’s nighttime anxiety is consistent rather than occasional: most nights, not just before a big test or during a hard week |
| → | You are required to stay in your child’s room until they fall asleep on most nights, and attempts to change this result in significant distress |
| → | Your child is consistently co-sleeping due to fear, not preference. This has been the pattern for weeks or months |
| → | Nighttime anxiety is producing significant daytime consequences: fatigue, school difficulty, irritability, avoidance of activities |
| → | Your child experiences recurrent nightmares that disrupt sleep and cause distress for multiple nights per week |
| → | The strategies you’ve tried (consistent routines, reassurance, environmental changes) haven’t produced improvement after about a month of consistent effort |
| → | Your gut says something more is going on. Parental instinct about their child’s functioning is clinically meaningful. Trust it. |
A professional evaluation doesn’t necessarily mean your child will need ongoing therapy. It means getting an accurate picture of what’s driving the nighttime anxiety: whether that’s a diagnosable anxiety disorder, a sleep disorder, a developmental factor, or a combination. Getting a clear map of what targeted intervention would actually look like.
Bedtime Shouldn’t Be the Hardest Part of the Day
If nighttime anxiety is disrupting your child’s sleep and your family’s peace, a conversation with a specialist is a reasonable next step. We’re here to help you figure out what’s going on and what will actually help.


